A clean heart scan may not mean what you think — a new study found plaque often starts somewhere else first.

Cardiovascular health assessments have long relied on the Coronary Artery Calcium (CAC) scan, a specialized X-ray test that provides a visual "score" of the calcium deposits within the walls of the coronary arteries. For decades, a score of zero—indicating no detectable calcified plaque—has been widely regarded by both clinicians and patients as a "clean bill of health." However, recent longitudinal research suggests that this clinical benchmark may offer a false sense of security, as it frequently overlooks the early-stage, non-calcified plaque that often develops in the carotid arteries or the aorta before manifesting in the heart itself.
The Mechanism of Atherosclerosis and Diagnostic Limitations
To understand why a clean heart scan can be misleading, one must first look at the biology of atherosclerosis. Plaque accumulation is a systemic, progressive inflammatory condition. It typically begins as "soft" or non-calcified plaque, consisting of lipids, cholesterol, and white blood cells. Over time, as the body attempts to repair this damage, calcium is deposited into the arterial walls, hardening the plaque.
The CAC scan is highly effective at identifying these late-stage, hardened deposits. However, the technology is inherently limited by its inability to visualize the soft, unstable plaque that characterizes the early stages of arterial disease. If a patient undergoes a CAC scan and receives a score of zero, they are often classified as low-risk. New evidence suggests that these individuals may still harbor significant atherosclerotic burden in other vascular beds, particularly the carotid arteries—the vessels supplying blood to the brain—or the thoracic aorta. This "blind spot" in cardiac screening means that patients who believe they are at minimal risk may, in fact, be at elevated risk for cardiovascular events or strokes, despite the clear coronary arteries.
Chronology of Diagnostic Evolution
The reliance on CAC scoring gained traction in the late 1990s and early 2000s, following landmark studies that established the test as a powerful predictor of future coronary events. It quickly became the gold standard for asymptomatic patient screening, often used to determine the necessity of statin therapy.
In the years that followed, medical societies, including the American College of Cardiology and the American Heart Association, integrated CAC scoring into risk assessment algorithms. By the mid-2010s, the medical community began to observe a subset of patients who, despite having zero coronary calcium, experienced acute myocardial infarctions. This discrepancy prompted a shift in research focus. Between 2020 and 2025, several multicenter studies utilized advanced imaging techniques, such as CT angiography and carotid ultrasound, to compare plaque distribution across the body. The findings were consistent: the absence of coronary calcium does not preclude the presence of systemic atherosclerosis.
Supporting Data and Statistical Trends
Data from recent clinical observations indicate that among patients aged 50 to 70 who present with a zero CAC score, nearly 10% to 15% may still show evidence of subclinical atherosclerosis in the carotid arteries. This is statistically significant because carotid plaque is a primary driver of ischemic stroke.
Furthermore, the "calcium paradox"—a term increasingly used in cardiology—highlights that calcium is a marker of healed or stable plaque rather than a marker of active disease progression. A patient with rapidly progressing soft plaque may have a zero CAC score because their arteries have not yet begun the calcification process. This group of patients is often at higher risk of plaque rupture, which leads to blood clots and sudden cardiac events, compared to those with stable, calcified plaque that has been present for years.
The Misconception of At-Home Maintenance
Parallel to these diagnostic advancements, public health concerns have intensified regarding the improper use of personal hygiene tools, specifically cotton swabs, which are often mistakenly used for ear canal maintenance. While seemingly unrelated to cardiovascular health, the cultural habit of "cleaning" internal body structures with inappropriate tools reflects a broader societal misunderstanding of physiological self-regulation.

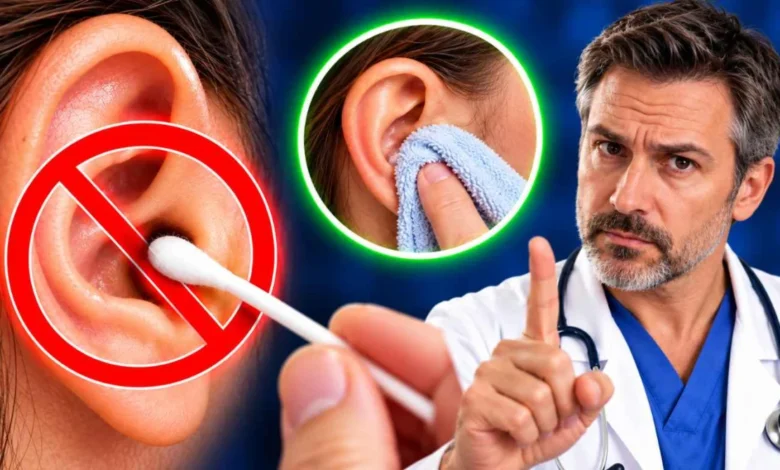
Dr. Alan Mandell and other medical professionals have repeatedly cautioned against the use of cotton swabs within the ear canal. The anatomy of the ear is designed for self-cleaning; the skin of the ear canal grows in a lateral migration pattern, moving dead skin cells and cerumen (earwax) outward. The use of a swab acts as a piston, compacting wax against the tympanic membrane (eardrum).
The analogy between the "clean" appearance of a swab and a "clean" heart scan is medically relevant: both are deceptive. Just as a swab tip covered in wax provides a false sense of cleanliness while pushing the bulk of the debris deeper, a clean CAC scan provides a false sense of systemic health while potentially ignoring the soft, non-calcified plaque buildup occurring elsewhere in the vascular system.
Official Responses and Clinical Guidelines
Medical bodies have begun to refine their guidance on cardiovascular risk. The consensus now leans toward a "holistic vascular assessment" rather than relying on a single screening tool. Clinical guidelines emphasize that while a zero CAC score is a strong indicator of low short-term risk, it should not be viewed in isolation. Physicians are now encouraged to incorporate traditional risk factors—such as blood pressure, lipid panels (specifically ApoB and LDL particle counts), family history, and systemic inflammation markers like high-sensitivity C-reactive protein (hs-CRP)—to create a more accurate patient profile.
Regarding the maintenance of the ear canal, the American Academy of Otolaryngology-Head and Neck Surgery has been definitive: "Don’t put anything smaller than your elbow in your ear." The official recommendation is that individuals should rely on the body’s natural migration of wax. If an individual experiences symptoms of impaction, such as muffled hearing, tinnitus, or vertigo, they are advised to seek professional irrigation rather than attempting home remedies.
Broader Implications for Preventive Medicine
The move away from viewing the CAC scan as an infallible indicator of health represents a maturation of preventive cardiology. The implication for patients is clear: health is not merely the absence of a single marker. It is a dynamic state that requires evaluating the body as an integrated system.
If a patient is high-risk due to genetic factors, diabetes, or hypertension, a zero CAC score should be treated as a baseline rather than a terminal point of inquiry. Future research is likely to shift toward "plaque burden" imaging, which assesses the total volume of all plaque types—calcified and non-calcified—rather than just the calcium component.
Ultimately, this paradigm shift serves as a reminder of the complexity of the human body. Whether dealing with the intricacies of vascular health or the delicate mechanics of the auditory system, the trend in modern medicine is toward respecting natural physiological processes and acknowledging the limitations of our current screening tools. Patients are encouraged to engage in active, informed dialogues with their primary care providers, ensuring that diagnostic results are interpreted within the context of their full clinical history, rather than as standalone guarantees of longevity.
Summary of Clinical Recommendations
- Contextualize Imaging: Always interpret a zero CAC score in the context of blood chemistry and lifestyle risk factors.
- Beyond Calcium: Recognize that soft plaque is a significant, yet often invisible, risk factor that requires aggressive management of lipids and blood pressure.
- Professional Care: For ear hygiene, abandon the use of internal swabs. If discomfort arises, professional medical removal is the only safe standard.
- Holistic Monitoring: Maintain a regular schedule of comprehensive physicals that monitor systemic inflammation, which is the underlying driver of both atherosclerosis and other chronic conditions.
As medical science progresses, the focus must remain on early detection through robust, evidence-based practices, ensuring that patients are not led astray by the superficial "cleanliness" of a scan or the temporary satisfaction of improper hygiene habits. True health outcomes are determined by long-term, systemic management rather than isolated data points.