Global Healthcare Blind Spot: Millions on Metformin Face Undiagnosed Vitamin B12 Deficiency and Reversible Neuropathy

Healthcare providers worldwide are consistently missing critical opportunities to prevent debilitating nerve damage by failing to monitor vitamin B12 levels in patients prescribed metformin, one of the most widely utilized medications for type 2 diabetes management. Despite widespread clinical recognition that the drug interferes with the absorption of cobalamin, routine screening remains remarkably rare. This systemic oversight leaves millions of patients vulnerable to secondary neuropathy—a painful, progressive condition that is frequently misattributed entirely to the underlying disease process of diabetes rather than to the pharmaceutical intervention used to treat it.
The scale of this issue has been brought into sharp focus by a comprehensive scoping review conducted by researchers at the School of Health Sciences at the University of Bath in the United Kingdom. Led by investigator Ian Parsonage, the research team analyzed data extracted from medical databases across the globe to map out current international clinical practice patterns regarding vitamin B12 monitoring. Published in the British Medical Journal, the findings reveal a stark disconnect between medical knowledge and practical application: fewer than 20 percent of diabetic patients undergoing long-term metformin therapy and categorized as being at high risk for neuropathy ever have their vitamin B12 status evaluated by their attending physicians.
In several individual studies evaluated within the broader review, the proportion of patients receiving adequate B12 screening dropped to an alarming 2 to 4 percent. These data points underscore a reactive rather than proactive clinical culture, where diagnostic testing is typically initiated only after patients present with overt, often advanced symptoms of nerve damage. For millions of individuals, this diagnostic delay means enduring preventable suffering from a condition that could otherwise be mitigated or entirely avoided through straightforward interventions.
The Mechanism of Deficiency and Clinical Consequences
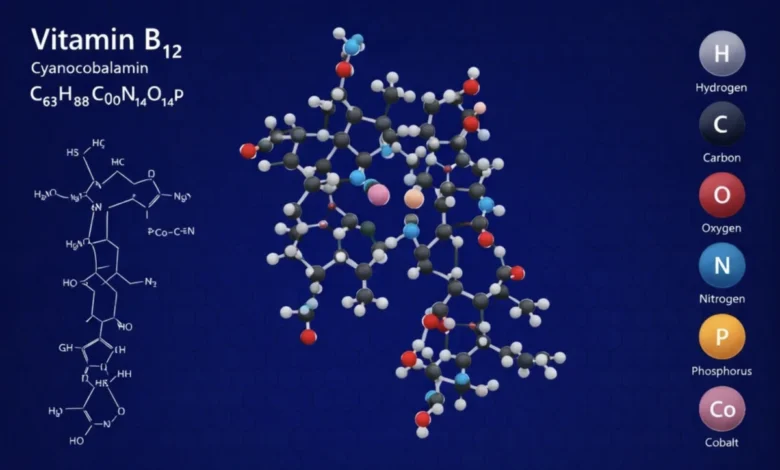
To understand the scope of the problem, medical experts point to the specific pharmacological interaction between metformin and human physiology. Metformin hydrochloride, prescribed to an estimated 17 million individuals in the United States alone and hundreds of millions more globally, acts primarily by reducing hepatic glucose production and improving insulin sensitivity. However, a major side effect of its long-term use is the disruption of calcium-dependent absorption of vitamin B12, also known as cobalamin, within the terminal ileum of the small intestine.
When cobalamin absorption is chronically impaired, cellular processes that depend on the vitamin begin to fail. This can result not only in peripheral neuropathy—characterized by numbness, tingling, burning, and sharp pain in the extremities—but also in megaloblastic anemia, a condition in which the bone marrow produces unusually large, structurally abnormal, immature red blood cells.
Because diabetic neuropathy is a well-established microvascular complication of diabetes itself, clinicians frequently struggle to differentiate between nerve damage caused by chronic hyperglycemia and nerve damage induced by drug-related micronutrient depletion. Making this distinction is vital, however, because neuropathy stemming from a vitamin B12 deficiency possesses a crucial clinical characteristic: unlike advanced diabetic neuropathy, it can frequently be halted, reversed, or significantly mitigated through targeted nutritional supplementation.
Integrative and functional medicine specialists have long raised alarms regarding this diagnostic overlap. Dr. Jacob Teitelbaum, a physician specializing in chronic pain and neurological conditions, estimates that out of the millions of neuropathy cases diagnosed in the United States, a substantial proportion—potentially numbering around 2.2 million—may be directly attributable or heavily exacerbated by metformin-induced B12 depletion rather than the disease process of diabetes alone. According to Teitelbaum, these cases represent a profound failure of preventative medicine, given how easily the underlying deficiency can be corrected.
Chronology of an Overlooked Interaction
The discovery of the link between biguanide medications and vitamin malabsorption is not a recent revelation, though its implementation in routine clinical care has lagged behind the science by decades.
The initial clinical case reports documenting a connection between metformin and declining vitamin B12 levels emerged in the medical literature during the 1970s. These early alerts were subsequently supported by observational studies throughout the 1980s and 1990s, which suggested a clear statistical correlation between prolonged drug exposure and biochemical markers of deficiency. Despite these early warnings, the medical community lacked large-scale, well-powered epidemiological trials to definitively quantify the risk on a global population level. Consequently, awareness remained largely academic, failing to penetrate daily primary care workflows.
It was not until the 2000s and 2010s that extensive epidemiological investigations began to solidify the statistical relationship. As the global prevalence of type 2 diabetes surged, pushing metformin prescriptions to near-ubiquitous levels as a first-line therapy, researchers gained the robust datasets necessary to analyze long-term outcomes.
A pivotal shift occurred in 2022, nearly half a century after the initial case reports, when government health regulators and major medical organizations—such as the United Kingdom’s Medicines and Healthcare products Regulatory Agency (MHRA)—began issuing formal, updated clinical guidance explicitly advising periodic monitoring of B12 levels for patients on long-term biguanide regimens. Despite these institutional updates, translation into frontline clinical practice has remained exceptionally sluggish.
Quantitative Insights: Duration and Risk Factors
Epidemiological studies published over the past decade provide precise metrics regarding the timeline and severity of metformin-induced B12 reduction. Prevalence estimates for the deficiency vary widely across clinical literature, ranging from 4 percent to 30 percent, largely depending on the biochemical thresholds utilized by different laboratories to define a deficit.

However, large-scale retrospective analyses have brought clarity to the risk profile. One of the most comprehensive epidemiological studies examining the phenomenon indicated that patients with type 2 diabetes taking metformin face a roughly 5 percent baseline increase in the risk of developing a clinically significant B12 deficiency compared to non-users. Furthermore, this risk is directly cumulative and scales with the duration of pharmacotherapy.
Statistical analyses demonstrate that each additional year of continuous metformin use is associated with a statistically significant 5 percent increase in the likelihood of developing a deficiency. Patients who maintain a continuous metformin regimen for four years or longer face a staggering 41 percent increase in their odds of developing a B12 deficiency compared to individuals who have been taking the medication for a shorter duration.
When tracking the downstream clinical endpoint of neuropathy, researchers have documented similarly striking relative risks. A large-scale analysis encompassing nearly 50,000 patients, conducted by researchers at the Peking University Health Science Center in Beijing, revealed that metformin-treated patients exhibited a neuropathy incidence rate of 7.12 per 1,000 person-years, compared to just 3.91 per 1,000 person-years in diabetic patients not utilizing the drug. The researchers estimated that metformin therapy conferred an 84 percent increased risk of developing neuropathy. Similarly, a clinical investigation conducted by researchers in Srinagar, India, documented neuropathic symptoms in 45 percent of metformin-treated patients, compared to 32 percent of control patients with diabetes who were not taking the medication.
Institutional Guidance and the Implementation Gap
Major medical bodies have gradually acknowledged these findings within their official practice guidelines, though critics argue the language remains overly broad and lacks actionable enforcement mechanisms.
The American Diabetes Association (ADA), in its updated Standards of Care guidelines, explicitly notes that individuals who have been prescribed metformin for more than four years, or who possess other baseline risk factors for cobalamin depletion, should be monitored for vitamin B12 deficiency on an annual basis. However, the ADA guidelines stop short of defining precise laboratory concentration thresholds for deficiency, nor do they outline standardized protocols for therapeutic repletion or neuropathy prevention.
Similarly, international academic committees have attempted to bridge the gap. In 2021, a research group led by Dr. Marco Infante at the Saint Camillus International University of Health Sciences in Rome published a comprehensive framework designed to establish cost-effective screening criteria for metformin-treated patients. Infante and his colleagues argued that because both vitamin B12 assays and oral supplementation are inexpensive, widespread implementation of systematic screening would yield massive cost savings for healthcare systems by preventing severe, costly neurological complications. Despite the publication of these rigorous frameworks, national and international public health agencies have been slow to incorporate them into mandatory quality-of-care metrics.
Systemic Barriers to Preventative Care
The scoping review by Parsonage and colleagues at the University of Bath highlights that the primary barrier is no longer a lack of professional awareness. In their synthesis of 23 distinct studies examining clinical practice patterns, the researchers found that a vast majority of physicians readily acknowledged the theoretical connection between metformin and vitamin B12 depletion.
Nevertheless, a substantial proportion of these same clinicians severely underestimated the clinical severity of the resulting deficiencies or failed to recall the critical diagnostic thresholds required to identify them on routine metabolic panels. Most concerningly, the data revealed a dangerous inverse relationship: the patient populations at the absolute highest risk for developing severe B12 deficiency—including geriatric patients, vegans, individuals prescribed high daily dosages of metformin, and those simultaneously taking proton pump inhibitors (PPIs) that further suppress gastric acid and nutrient absorption—were consistently found to be the least likely to undergo routine B12 screening.
When queried about the persistence of this clinical gap, physicians frequently cited systemic barriers, including a lack of electronic health record prompts, institutional anxieties regarding the marginal cost of additional laboratory tests, and an overwhelming number of competing clinical priorities during standard diabetes management consultations.
Implications and the Path Forward
The University of Bath research team emphasizes that educational outreach alone will not resolve the crisis. Meaningful progress will require structural, system-wide interventions designed to automate and mandate preventative monitoring. Proposed systemic solutions include the introduction of mandatory electronic health record (EHR) clinical decision support prompts, the revision of institutional clinical pathways, targeted educational workshops for primary care providers, and the routine integration of vitamin B12 status checks into standardized annual diabetes management checklists.
While overhauling healthcare infrastructure is a notoriously protracted process, medical specialists urge frontline practitioners to adopt immediate, pragmatic safeguards. Dr. Teitelbaum advocates for a preemptive approach that bypasses the complexities of frequent blood testing where resources are constrained, noting that simple nutritional supplementation can dramatically reduce patient risk without the burden of excessive medical expenditures.
"Simple measures could prevent much of the toxicity caused by diabetes and its treatments," Teitelbaum notes. "It is highly recommended that individuals prescribed long-term metformin therapy take a standard multivitamin containing at least 100 micrograms of vitamin B12. Beyond protecting nerve function, this simple preventative step can safeguard against numerous other nutrient depletions common in chronic metabolic disease."
As the global burden of type 2 diabetes continues to rise, closing the gap between pharmacological management and micronutrient surveillance remains an urgent priority for modern clinical practice. Without systemic reforms to ensure routine B12 monitoring, millions of patients will remain at avoidable risk of progressive, irreversible neurological harm.