Living with Irritable Bowel Syndrome: A Comprehensive Guide to Understanding, Managing, and Improving Quality of Life

Irritable Bowel Syndrome (IBS) stands as the most prevalent digestive disorder globally, affecting an estimated 14 percent of the adult population. Despite its widespread nature, the condition remains shrouded in stigma and physical discomfort, significantly impacting the day-to-day existence of millions. Recent data underscores the severity of the burden: a study of nearly 2,000 individuals living with IBS revealed that a significant portion would willingly trade 10 to 15 years of their life expectancy for an immediate and permanent cure. Furthermore, research into patient trade-offs has shown that some individuals would accept a one percent risk of sudden death in exchange for the elimination of their symptoms.
These stark statistics highlight the profound toll of a condition characterized by urgent bouts of diarrhea, persistent constipation, debilitating gas, and abdominal pain—the latter of which some patients describe as exceeding the intensity of childbirth. This chronic distress creates a cycle of "gastrointestinal-specific anxiety," forcing patients to curate their entire lives around the proximity of private, sanitary restrooms. The resulting social isolation, reduced work productivity, and compromised mental health often lead to a lower self-reported quality of life than that observed in patients with chronic heart disease, diabetes, or end-stage kidney disease.
The Evolution of Understanding: From Psychological Label to Neuro-Gastrointestinal Disorder
For decades, the medical community frequently categorized IBS as a purely psychosomatic condition. Because diagnostic imaging—including colonoscopies and biopsies—typically reveals no visible structural damage, inflammation, or infection, the "spastic colon" label was often dismissed as a manifestation of stress rather than a physical pathology.

This paradigm has shifted significantly in recent years. Modern medicine now classifies IBS as a functional neuro-gastrointestinal disorder. This definition acknowledges that the communication pathways between the gastrointestinal tract and the brain are not functioning optimally. Rather than structural decay, the problem lies in "software" malfunctions: the brain sends inappropriate pain signals, and the gut’s nervous system fails to process these signals or coordinate muscular contractions effectively.
The Mechanism of Discomfort: Why the Gut Reacts
Researchers have identified several primary hypotheses regarding why the gut functions erratically in IBS patients. The most prominent theory centers on visceral hypersensitivity. In a healthy digestive system, the transit of gas or the contraction of muscles is largely unnoticed. In an IBS patient, however, the nerve endings in the GI tract are hypersensitive. Tiny, normal gas bubbles can trigger significant pain, and GI muscles may contract with excessive force—leading to spasms and diarrhea—or insufficient force, resulting in sluggish transit and constipation.
A secondary area of intense research involves the gut microbiome. Many patients report the onset of IBS symptoms following a severe gastrointestinal illness, such as the Norovirus. This suggests that a singular, acute disruption to the microbial ecosystem can result in long-term, chronic dysfunction, effectively altering the "internal landscape" of the gut.
Diagnostic Challenges and the Role of the Professional
Diagnosing IBS remains a challenge because its symptoms—abdominal pain, cramping, and stool irregularities—overlap with serious organic diseases, including Celiac disease, inflammatory bowel disease (IBD), and colorectal cancer. Consequently, medical guidelines mandate that clinicians rule out "red flag" symptoms before confirming an IBS diagnosis. These warning signs include unexplained weight loss, blood in the stool, nighttime diarrhea, and a family history of colon cancer.

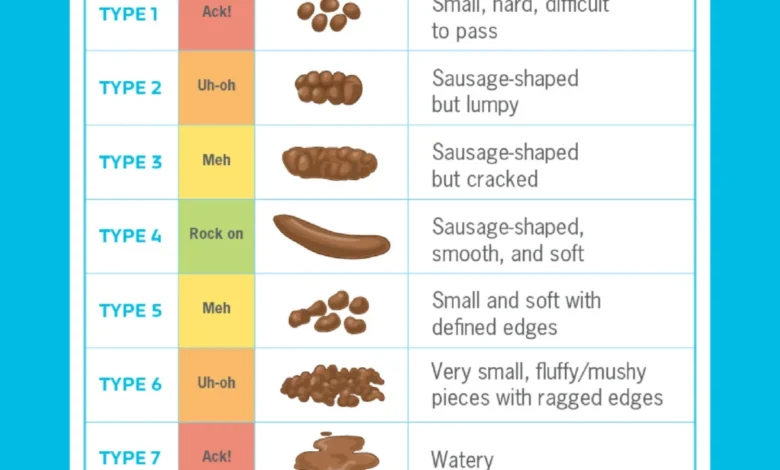
Patients are encouraged to maintain a detailed "poo diary" prior to clinical appointments. Utilizing the Bristol Stool Chart—a standard medical tool that classifies stool consistency from type 1 (hard lumps) to type 7 (watery)—helps healthcare providers categorize the specific type of IBS: IBS-C (constipation-predominant), IBS-D (diarrhea-predominant), or IBS-M (mixed). This classification is essential for determining whether a patient might benefit from fiber supplements, antidiarrheal medications, or specialized pharmacological interventions that regulate gut motility.
Strategic Management: Evidence-Based Lifestyle Interventions
While there is no "cure" for IBS, a multifaceted, evidence-based approach can significantly mitigate symptoms. PN Super Coach Sarah Maughan, a specialist certified through Monash University, emphasizes that lifestyle changes often provide the foundation for long-term symptom management.
- The Role of Movement: Clinical studies have demonstrated that moderate exercise, such as walking for one hour three times a week, significantly reduces bloating and pain within 12 weeks. Exercise appears to improve the gut-brain axis, potentially by lowering circulating stress hormones and fostering a healthier gut microbiome.
- Stress Regulation: Stress is a primary trigger for flare-ups. Elevated levels of cortisol and norepinephrine alter gut motility and increase intestinal sensitivity. Techniques such as diaphragmatic breathing, yoga, and meditation—when framed as nervous system regulation rather than mere "relaxation"—help patients shift their focus to what they can control, reducing the feedback loop between anxiety and digestive distress.
- Optimizing Eating Habits: The pace at which one consumes food is critical. Slower eating and thorough chewing assist in the mechanical breakdown of food and stimulate digestive enzymes, reducing the workload on the stomach and intestines. Furthermore, eating in a calm environment minimizes the sympathetic nervous system response that often exacerbates GI symptoms.
- Sleep Hygiene: There is a well-documented correlation between IBS and poor sleep quality. Insufficient rest elevates stress hormones, which in turn intensifies gut pain, creating a self-perpetuating cycle. Improving sleep hygiene—through consistent routines, temperature control, and limiting food intake shortly before bed—is a crucial, if often overlooked, therapeutic strategy.
- Dietary Investigation: The "one-size-fits-all" diet does not exist for IBS. However, many individuals find relief by managing intake of high-FODMAP foods—a group of fermentable carbohydrates that are poorly absorbed and can cause osmotic pressure and gas in the small intestine. Other common triggers include caffeine, alcohol, spicy foods, and artificial sweeteners like sorbitol.
The Science of Elimination Diets
An elimination diet acts as a controlled experiment. By systematically removing potentially problematic foods for a period of two to three weeks and then reintroducing them one by one, patients can identify their personal "trigger" foods.
For those with severe sensitivity, the Monash University-developed Low-FODMAP diet is considered the gold standard of medical nutrition therapy. However, this is a complex, restrictive protocol that should only be undertaken with the guidance of a registered dietitian or a certified practitioner. For many others, an "elimination lite" approach—removing only the most likely culprits—can yield significant results without requiring a total overhaul of the patient’s diet.

The Value of Professional Health Coaching
The gap between "knowing" what to do and "executing" those changes is where health coaching proves most valuable. A coach does not diagnose or prescribe, but rather empowers the client to experiment with their lifestyle in a structured, safe manner.
A coach helps a client bridge the divide between their clinical diagnosis and their daily habits. For instance, while a doctor may recommend an elimination diet, a coach provides the practical tools, recipes, and accountability necessary to adhere to the plan. Crucially, the coach helps reframe the relationship with food: learning that a specific food triggers a reaction is not a "failure" or a lifelong ban; it is data. This knowledge provides the patient with the autonomy to make informed choices, deciding when to avoid a trigger and when to consume it, thereby reclaiming a sense of control over their body.
Implications and Future Outlook
The burden of IBS on the healthcare system and the individual is immense, yet the shift toward personalized, multidisciplinary care is promising. By moving away from the outdated psychological stigma and toward a model that integrates medical supervision, dietary strategy, and lifestyle management, patients are increasingly able to navigate their condition with greater agency.
For the healthcare industry, the focus must remain on early diagnosis and the integration of behavioral health with gastroenterology. As the understanding of the gut-brain axis deepens, it is likely that future treatments will move beyond symptom management toward interventions that address the underlying neural and microbial dysfunctions. For the millions currently suffering, the message remains clear: while IBS is a chronic condition, it is not an unmanageable one. With the right support system, clinical guidance, and a commitment to understanding the body’s unique signals, a significant improvement in quality of life is achievable.